🇸🇪 Svenska · 🇬🇧 English · 🇪🇸 Español
Originally published in Swedish on 18 November 2026.
A Swedish doctor has an average of about three registered patient contacts per working day. Ten years ago, the figure was 3.9. At the same time, the number of doctors has risen sharply—without patient contacts increasing at a corresponding rate. We employ more doctors but get fewer patient encounters per doctor. How did we manage that?
More doctors—but not more care
Healthcare should be judged by how much care patients receive, how quickly they receive it and how good the outcomes are. Not by the number of employees or how many billions politicians can boast that they have invested.
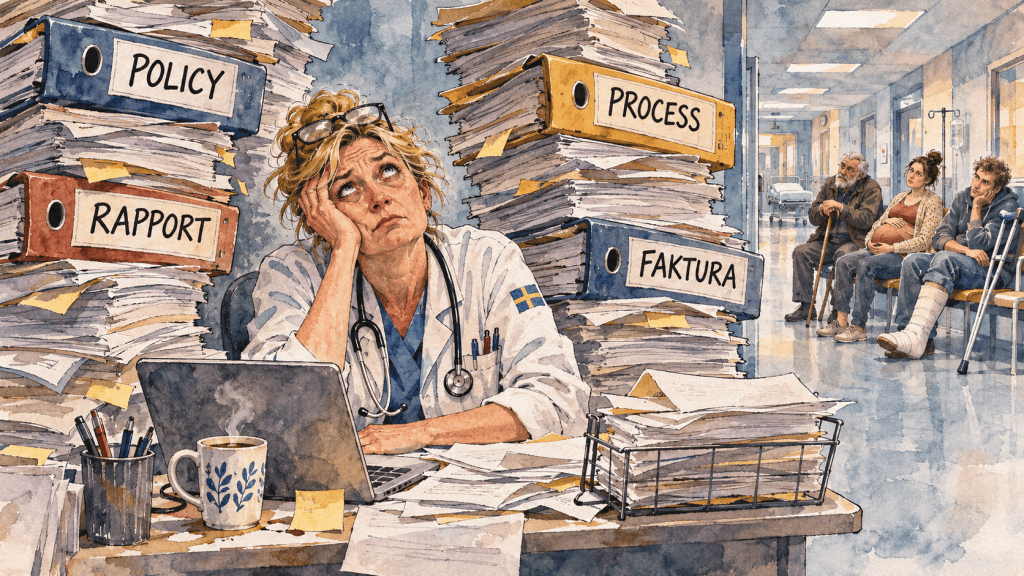
No one needs to convince me that doctors sit idle. They perform surgery, care for inpatients and do much more besides consultations. The problem is that the system fills their days with an ever-growing number of tasks that are not healthcare.
Case officers increase—patient encounters do not
Between 2015 and 2025, the number of case officers employed by Sweden’s regions increased by 46 per cent. Staff engaged in management work increased by 25 per cent. New processes, control systems, follow-ups, documentation requirements and policy documents must be produced, reviewed and evaluated.
Eventually, documenting that work has been done becomes more important than actually getting the work done.
SEK 125 billion more—what did patients get?
In 2015, the regions’ net healthcare costs were just over SEK 219 billion. In 2025, they were about SEK 343.5 billion. That is an increase of roughly SEK 125 billion a year—57 per cent in ten years.
Prices and wages have of course risen. The population has also aged, and healthcare can treat more complicated diseases. But that does not change the question taxpayers must be allowed to ask: How much more care do we receive for all these billions? Registered patient contacts per doctor are moving in the wrong direction while the bill grows.
The amounts refer to the regions’ net costs excluding medicines covered by the pharmaceutical benefits scheme, at current prices. The 2025 figure excludes Gotland. Sources: SOU 2021:89 and SOU 2026:61.
The cost per doctor’s visit is soaring
If we divide the regions’ net costs by the number of registered doctor’s visits, the contrast becomes even clearer. In 2015, it was equivalent to about SEK 7,700 per doctor’s visit. In 2025, about SEK 11,500. That is almost 50 per cent more per registered visit.
This does not mean that a doctor’s visit itself costs SEK 11,500. The amount also includes hospital care, operations, nursing and all other healthcare activities. But as a measure of how total healthcare costs are developing in relation to the number of doctor’s visits, the comparison is highly relevant.
Calculation: approximately SEK 219 billion divided by 28–29 million doctor’s visits in 2015, and SEK 343.5 billion divided by approximately 30 million visits in 2025. The visit figures are estimates, and changed definitions of remote contacts make the comparison approximate.
Stop feeding bureaucracy more billions
Whenever healthcare problems are discussed, the same demand appears: more money. But why should taxpayers continue to finance a system in which administration grows while output per doctor falls?
Doctors should not have to spend valuable working time on invoicing, duplicate registration and reports that others could handle—or that do not need to be produced at all. A procedure should exist only if it contributes to better care, greater patient safety or lower costs. The rest must go.
Measure patient benefit—not the number of action plans
We should measure how many patients actually receive treatment, waiting times, outcomes and cost per treatment. Then demand that the trend moves in the right direction.
Hiring a thousand new doctors is not a success if patients notice no improvement. Hiring more managers who produce more reports about the same old waiting lists is not a success either.
Swedish healthcare needs fewer processes, fewer policy documents and less administrative nonsense. The purpose of healthcare is to care for people, not to administer itself.
We must get more care for the money. Not less care for more money.
Sources and clarification
SKR’s personnel statistics show the increase in case officers and management work from 2015 to 2025. SKR’s activity statistics and the OECD comparison describe patient contacts. Three and 3.9 contacts per working day are estimates, with differences in registration between the years; they do not include all patient work. The case-officer figure covers all regional operations, not healthcare alone.
Image: AI-generated illustration.


Lämna ett svar